Transgender Breast Augmentation

Creating a feminine breast shape through individualized surgical planning.

Breast augmentation can be an important part of gender affirmation, helping transgender women achieve a breast shape that reflects their personal goals. Creating that shape involves more than adding volume: existing breast tissue, chest proportions and the relationship between the nipples and breast folds all influence the result.

At WIH International Hospital in Bangkok, Thailand, our plastic surgery team plans breast augmentation around each patient’s anatomy, preferences and recovery needs. Individualized surgical planning is supported by coordinated anesthesia, nursing and postoperative care.

The team includes Dr. Chettasak Tulayaphanich, whose more than 30 years of experience in transgender surgery encompasses both breast augmentation and genital gender-affirming surgery.

Whether the desired change is subtle or more pronounced, the aim is to create breasts that suit the patient’s proportions, with careful attention to contour, nipple alignment and implant support.


Transgender Breast Augmentation

Creating a feminine breast shape through individualized surgical planning.

Breast augmentation can be an important part of gender affirmation, helping transgender women achieve a breast shape that reflects their personal goals. Creating that shape involves more than adding volume: existing breast tissue, chest proportions and the relationship between the nipples and breast folds all influence the result.

At WIH International Hospital in Bangkok, Thailand, our plastic surgery team plans breast augmentation around each patient’s anatomy, preferences and recovery needs. Individualized surgical planning is supported by coordinated anesthesia, nursing and postoperative care.

The team includes Dr. Chettasak Tulayaphanich, whose more than 30 years of experience in transgender surgery encompasses both breast augmentation and genital gender-affirming surgery.

Whether the desired change is subtle or more pronounced, the aim is to create breasts that suit the patient’s proportions, with careful attention to contour, nipple alignment and implant support.
Transgender Breast Augmentation

Creating a feminine breast shape through individualized surgical planning.

Breast augmentation can be an important part of gender affirmation, helping transgender women achieve a breast shape that reflects their personal goals. Creating that shape involves more than adding volume: existing breast tissue, chest proportions and the relationship between the nipples and breast folds all influence the result.

At WIH International Hospital in Bangkok, Thailand, our plastic surgery team plans breast augmentation around each patient’s anatomy, preferences and recovery needs. Individualized surgical planning is supported by coordinated anesthesia, nursing and postoperative care.

The team includes Dr. Chettasak Tulayaphanich, whose more than 30 years of experience in transgender surgery encompasses both breast augmentation and genital gender-affirming surgery.

Whether the desired change is subtle or more pronounced, the aim is to create breasts that suit the patient’s proportions, with careful attention to contour, nipple alignment and implant support.
Why Individualized Planning Matters

Transgender and cisgender breast augmentation share the same fundamental surgical principles. However, the starting anatomy can vary considerably among transgender women—from limited breast tissue over a broad chest to well-developed breasts following hormone therapy.

These differences affect implant coverage, breast projection, cleavage and the shape of the lower breast. The same implant size or surgical technique can therefore produce different results in different patients.

A meaningful consultation connects the appearance a patient hopes to achieve with the possibilities and limitations of her anatomy. The surgical assessment considers five factors together: existing breast tissue, chest width, nipple position, the pectoralis muscle and the inframammary fold.

Breast Development Following Hormone Therapy

Estrogen can produce meaningful breast development, but the amount and timing vary. Some patients achieve the volume they want through hormone therapy, while others consider augmentation for additional fullness or a different contour.

Published research illustrates this variation:

StudyParticipantsObservation periodMain finding
de Blok et al., 2018229 transgender womenOne year48.7% had a calculated cup size below AAA.
de Blok et al., 202169 transgender womenThree yearsBreast volume continued to increase; 71% had a calculated cup size below A.

These studies involved different cohorts and measurement methods, so their percentages should not be compared directly. The findings provide context rather than predict an individual patient’s development.

Limited breast development does not necessarily indicate inadequate hormone treatment. The amount of existing tissue, the stage of development and the patient’s goals should all inform the timing and planning of surgery.

Five Anatomical Factors That Shape the Surgical Plan

1. Existing Breast Tissue — Coverage and Natural Contour

Existing breast tissue contributes to the final breast volume and provides coverage over the implant. When development is substantial, a moderate implant may provide the desired enhancement while working with the shape already present.

When tissue is limited, the implant creates more of the breast mound. Its dimensions and placement require particular attention to avoid an abrupt transition from the chest to the breast or excessive visibility of implant edges.

Limited tissue does not automatically mean that a larger implant is better. Chest width, skin flexibility and the available space for expansion must also be considered.

Patient Example — 380 cc Breast Implants
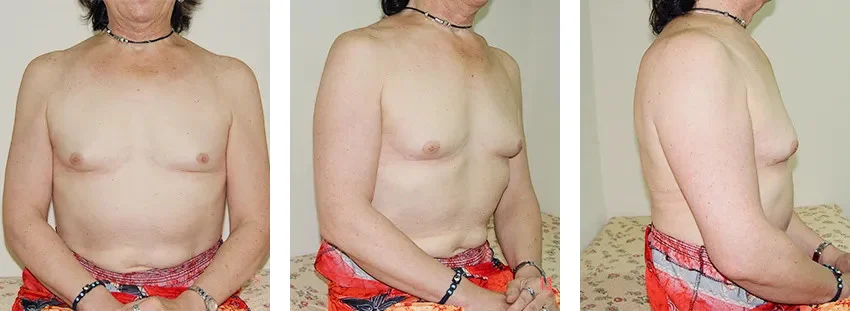
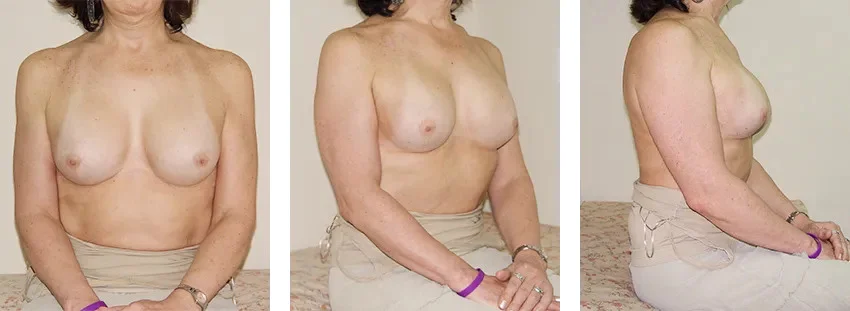
18-year-old patient from France

breast-augmentation-380cc-dr-chettasak-before-surgery

Before Surgery

breast-augmentation-380cc-dr-chettasak-after-surgery

After Surgery

This case illustrates how implant selection complements existing breast tissue and chest proportions. Individual results vary.

Surgery by Dr. Chettasak Tulayaphanich · WIH International Hospital

2. Chest Width — Matching the Implant to Body Proportions

Chest width helps determine the appropriate implant base. On a broad chest, a narrow implant may create a prominent but relatively small breast mound that does not balance the surrounding torso.

Implant selection therefore considers width, projection and volume together. A broader implant may provide a more proportionate footprint, while its projection determines how much fullness extends forward.

Some patients with a broad chest may need a larger implant to achieve their desired proportions. However, there is no minimum implant size for transgender breast augmentation. The final choice depends on measured anatomy, tissue coverage and the dimensions of the selected model.

Patient Example — 600 cc Breast Implants
59-year-old patient from France

Breast-implant-surgery-600cc-Doctor-Chettawut-breast-augmnetation-gallery-before-surgery

Before Surgery

Broad-chest anatomy before breast augmentation with 600 cc implants at WIH Hospital

Breast-implant-surgery-600cc-Doctor-Chettawut-breast-augmnetation-gallery-after-surgery

After Surgery

Broad-chest result after breast augmentation with 600 cc implants at WIH Hospital

This case illustrates how implant selection complements existing breast tissue and chest proportions. Individual results vary.

Surgery by Dr. Chettasak Tulayaphanich · WIH International Hospital

3. Nipple Position — Balancing Cleavage and Breast Alignment

Nipple position is especially important when discussing cleavage. Widely spaced nipples affect where each implant should sit to keep the nipple naturally aligned with the new breast mound.

Standard implant augmentation does not directly relocate the nipple–areola complex. Positioning the implants closer to the center may improve medial fullness, but excessive inward positioning can make the nipples appear too far toward the outer edges of the breasts.

The surgical plan balances the desired cleavage with nipple alignment and the normal separation between the breasts. These anatomical limits are discussed during consultation so that expectations are realistic.

breast-augmentation-320cc-dr-chettasak-before-surgery

Before Surgery

breast-augmentation-320cc-dr-chettasak-after-surgery-Post-op 3 months

After Surgery

This case demonstrates a well-balanced result, combining the desired cleavage with proper nipple alignment and a natural separation between the breasts.. Individual results vary.

Surgery by Dr. Chettasak Tulayaphanich · WIH International Hospital

4. Pectoralis Major — Coverage, Projection and Muscle Tension

The pectoralis major is the large chest muscle that can cover the upper portion of an implant. Its thickness and tightness influence both implant selection and pocket creation.

Muscle coverage can be useful when breast tissue is limited, helping soften the transition at the upper breast. A thick or tight muscle may also restrict projection or lower-breast expansion if the pocket is inadequately released.

Assessment includes observing the muscle at rest and during contraction. The surgeon then considers implant projection, controlled muscle release and whether a dual-plane modification is appropriate.

Placement beneath the muscle involves trade-offs. These include muscle-related discomfort during recovery and possible breast movement when the muscle contracts, known as animation deformity.

Patient Example — 600 cc Breast Implants
26-year-old patient from Finland

Breast-implant-surgery-600cc--Doctor-Chettawut-breast-augmnetation-gallery-before-surgery

Before Surgery

Breast-implant-surgery-600cc--Doctor-Chettawut-breast-augmnetation-gallery-after-surgery-5--years

After Surgery

This case illustrates how implant selection and pocket planning account for pectoralis muscle characteristics. Individual results vary.

Surgery by Dr. Chettasak Tulayaphanich · WIH International Hospital

5. Inframammary Fold and Lower Pole — Establishing the Breast Foundation

The inframammary fold, or IMF, is the crease beneath the breast. It defines the lower boundary of the breast mound and influences the relationship between implant position and nipple height.

Some transgender patients have a high fold and a short, tight lower breast. If this space cannot accommodate the selected implant, the implant may sit too high and the lower contour may remain insufficiently developed.

In suitable cases, the fold needs to be lowered. This requires careful measurement and controlled release of restrictive tissues.

Insufficient release may leave the implant high. Excessive lowering may allow it to descend too far, causing bottoming out. Planning considers implant dimensions and the stretched nipple-to-fold distance, with reassessment of breast shape during surgery.

Patient Example — 380 cc Breast Implants 23-year-old patient from Thailand

breast-augmentation-300cc-dr-chettasak-before-surgery

Before Surgery

breast-augmentation-300cc-dr-chettasak-after-surgery-post-op 6 months

After Surgery

Surgery by Dr. Chettasak Tulayaphanich · WIH International Hospital

Choosing Breast Implants Together

Implant selection is a shared decision. The patient’s preferences guide the desired appearance, while clinical measurements help identify options that can be appropriately covered and supported.

Implant Brand and Model

Implant options discussed at WIH include Motiva Ergonomix2 through the JOY program and Mentor MemoryGel Xtra.

The consultation explains relevant differences between available models, including dimensions, projection and gel characteristics. The recommendation considers how these features relate to the patient’s tissues and desired contour.

Current availability, product information and warranty terms are reviewed when the treatment plan is finalized.

Motiva and Mentor breast implant options discussed at WIH Hospital

Width, Projection and Volume

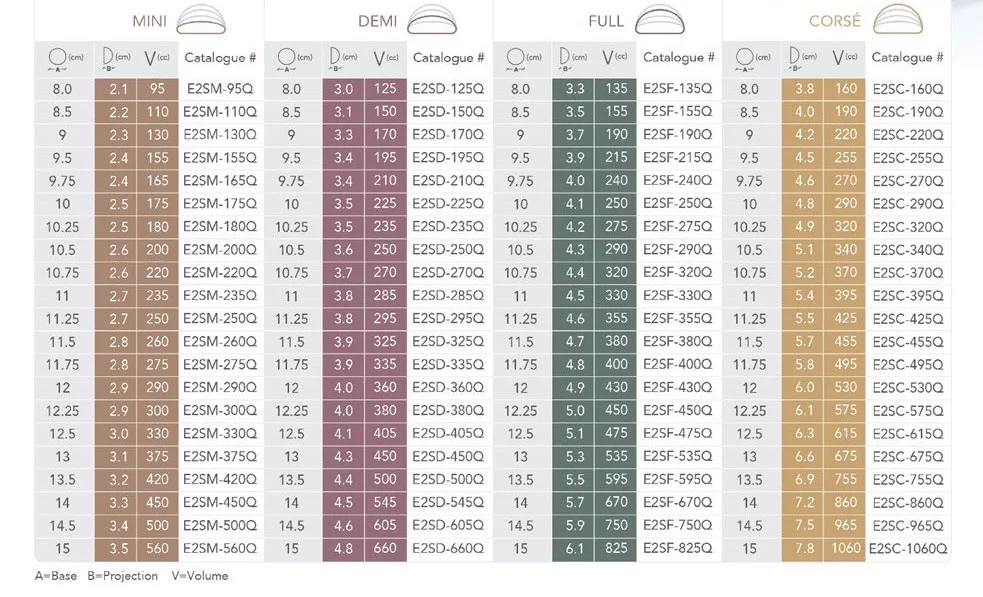
Volume is only one part of implant selection. Two implants with similar volumes may have different widths and projections, producing different effects on the same chest.

CharacteristicWhat it means for planning
Base widthThe implant’s footprint and how it fits the available breast base.
ProjectionHow far the implant extends forward from the chest.
VolumeAdded fullness, considered alongside width and projection.
Gel and model characteristicsFeatures influencing implant feel and shape behavior.
Tissue coverageHow well surrounding tissues can conceal and support the implant.
Size-Motiva-joy

The selected combination should fit the patient’s proportions and preferences while respecting tissue limitations.

Visualizing the Desired Result

Reference photographs, external implant sizers and simulation tools help patients communicate their preferences.

These tools cannot predict exactly how tissues will stretch or how the implant will settle. A particular implant volume also cannot guarantee a specific bra cup size, which varies with chest measurements and bra brands.

Choosing the Incision: Where Will the Scar Be?

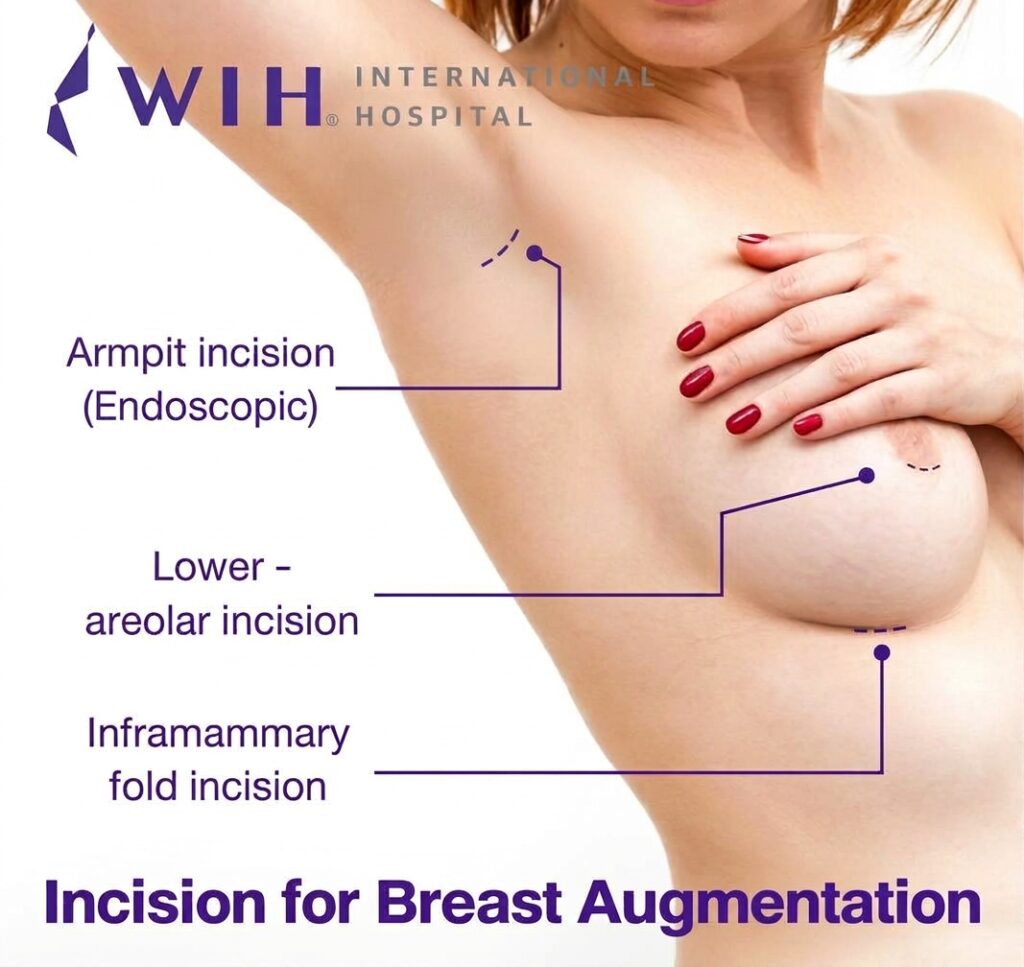
Scar preference matters, but the incision must also provide suitable access for implant insertion, pocket dissection and any necessary fold adjustment.

ApproachScar locationMain considerations
InframammaryIn the crease beneath the breastDirect access for pocket creation and IMF control. Scar placement must account for the intended final fold.
Endoscopic transaxillaryIn the underarmAvoids an incision on the breast itself. Endoscopic visualization supports pocket dissection and controlled release.
PeriareolarAlong part of the areolar borderRequires suitable areolar dimensions. Smaller areolae may limit access for implant insertion.
Breast Augmentation Incision Options at WIH International Hospital

Breast Augmentation Incision Options at WIH International Hospital

The underarm approach is an excellent choice for patients who want to avoid a scar on the breast. The incision is placed within a natural underarm crease and may become barely noticeable over time.

Incision-for-Breast-Augmentation

This case demonstrates a well-faded underarm scar that is barely visible at the one-year follow-up after breast augmentation.

Above or Below the Muscle? Understanding Implant Placement

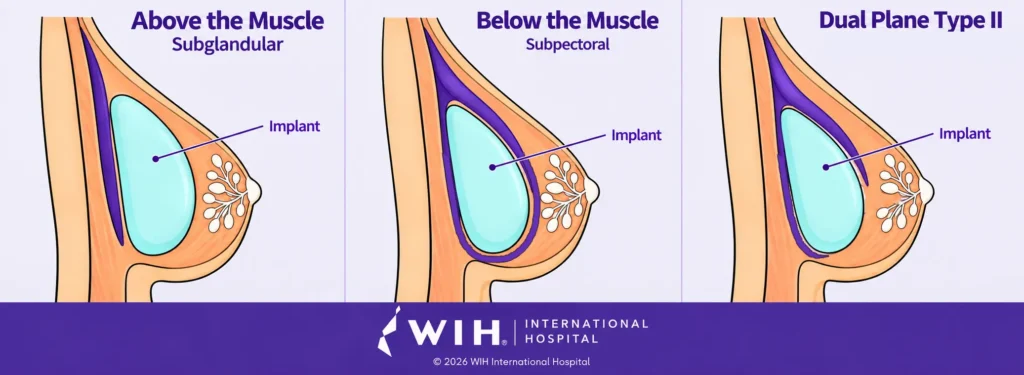
The implant plane describes which tissues cover the implant. It is selected according to breast tissue thickness, muscle characteristics, skin flexibility and the desired shape.

Subglandular and Subfascial Placement — Above the Muscle

Subglandular placement positions the implant beneath the breast tissue and above the pectoralis muscle. It may be suitable when existing tissue provides adequate coverage or when some degree of breast droop needs to be considered. Muscle-related implant movement is avoided, but thin coverage can make implant edges or rippling more visible.

Subfascial placement positions the implant just beneath the pectoral fascia, the layer between the breast tissue and the pectoralis muscle. Because this fascia is very thin, it adds no meaningful layer of coverage, so subfascial placement behaves much like subglandular placement in practice.

Subpectoral Placement — Beneath the Muscle

Subpectoral placement provides muscle coverage over part of the implant and is often considered when breast tissue is limited.

Planning must account for muscle tightness, implant projection and lower-pocket release. Muscle-related discomfort and animation are important considerations.

Dual-Plane Placement — Combining Coverage with Lower-Breast Expansion

Dual-plane augmentation combines upper muscle coverage with a lower implant portion beneath the breast tissue. Controlled release allows the lower breast to accommodate the implant.

Different modifications involve different amounts of tissue separation. The surgeon selects the appropriate modification according to the anatomy and planned contour.

Comparison of 3 breast implant placement planes: Above the Muscle (Subglandular), Below the Muscle (Subpectoral), and Dual Plane Type II, showing muscle coverage and implant positioning.

Comparison of 3 breast implant placement planes:
Above the Muscle (Subglandular), Below the Muscle (Subpectoral), and Dual Plane Type II, showing muscle coverage and implant positioning.

Width, Projection and Volume

Volume is only one part of implant selection. Two implants with similar volumes may have different widths and projections, producing different effects on the same chest.

CharacteristicWhat it means for planning
Base widthThe implant’s footprint and how it fits the available breast base.
ProjectionHow far the implant extends forward from the chest.
VolumeAdded fullness, considered alongside width and projection.
Gel and model characteristicsFeatures influencing implant feel and shape behavior.
Tissue coverageHow well surrounding tissues can conceal and support the implant.
Size-Motiva-joy

The selected combination should fit the patient’s proportions and preferences while respecting tissue limitations.

Visualizing the Desired Result

Reference photographs, external implant sizers and simulation tools help patients communicate their preferences.

These tools cannot predict exactly how tissues will stretch or how the implant will settle. A particular implant volume also cannot guarantee a specific bra cup size, which varies with chest measurements and bra brands.

Choosing the Incision: Where Will the Scar Be?

Scar preference matters, but the incision must also provide suitable access for implant insertion, pocket dissection and any necessary fold adjustment.

ApproachScar locationMain considerations
InframammaryIn the crease beneath the breastDirect access for pocket creation and IMF control. Scar placement must account for the intended final fold.
Endoscopic transaxillaryIn the underarmAvoids an incision on the breast itself. Endoscopic visualization supports pocket dissection and controlled release.
PeriareolarAlong part of the areolar borderRequires suitable areolar dimensions. Smaller areolae may limit access for implant insertion.
Breast Augmentation Incision Options at WIH International Hospital

Breast Augmentation Incision Options at WIH International Hospital

An underarm approach still leaves an underarm scar. Scar visibility varies with skin characteristics, healing and postoperative care.

Underarm scar at 1-year follow-up after breast augmentation.

Incision-for-Breast-Augmentation

This case demonstrates a well-faded underarm scar that is barely visible at the one-year follow-up after breast augmentation.

Above or Below the Muscle? Understanding Implant Placement

The implant plane describes which tissues cover the implant. It is selected according to breast tissue thickness, muscle characteristics, skin flexibility and the desired shape.

Subglandular and Subfascial Placement — Above the Muscle

Subglandular placement positions the implant beneath the breast tissue and above the pectoralis muscle. It may be suitable when existing tissue provides adequate coverage or when some degree of breast droop needs to be considered. Muscle-related implant movement is avoided, but thin coverage can make implant edges or rippling more visible.

Subfascial placement positions the implant just beneath the pectoral fascia, the layer between the breast tissue and the pectoralis muscle. Because this fascia is very thin, it adds no meaningful layer of coverage, so subfascial placement behaves much like subglandular placement in practice.

Subpectoral Placement — Beneath the Muscle

Subpectoral placement provides muscle coverage over part of the implant and is often considered when breast tissue is limited.

Planning must account for muscle tightness, implant projection and lower-pocket release. Muscle-related discomfort and animation are important considerations.

Dual-Plane Placement — Combining Coverage with Lower-Breast Expansion

Dual-plane augmentation combines upper muscle coverage with a lower implant portion beneath the breast tissue. Controlled release allows the lower breast to accommodate the implant.

Different modifications involve different amounts of tissue separation. The surgeon selects the appropriate modification according to the anatomy and planned contour.

Comparison of 3 breast implant placement planes: Above the Muscle (Subglandular), Below the Muscle (Subpectoral), and Dual Plane Type II, showing muscle coverage and implant positioning.

Comparison of 3 breast implant placement planes:
Above the Muscle (Subglandular), Below the Muscle (Subpectoral), and Dual Plane Type II, showing muscle coverage and implant positioning.

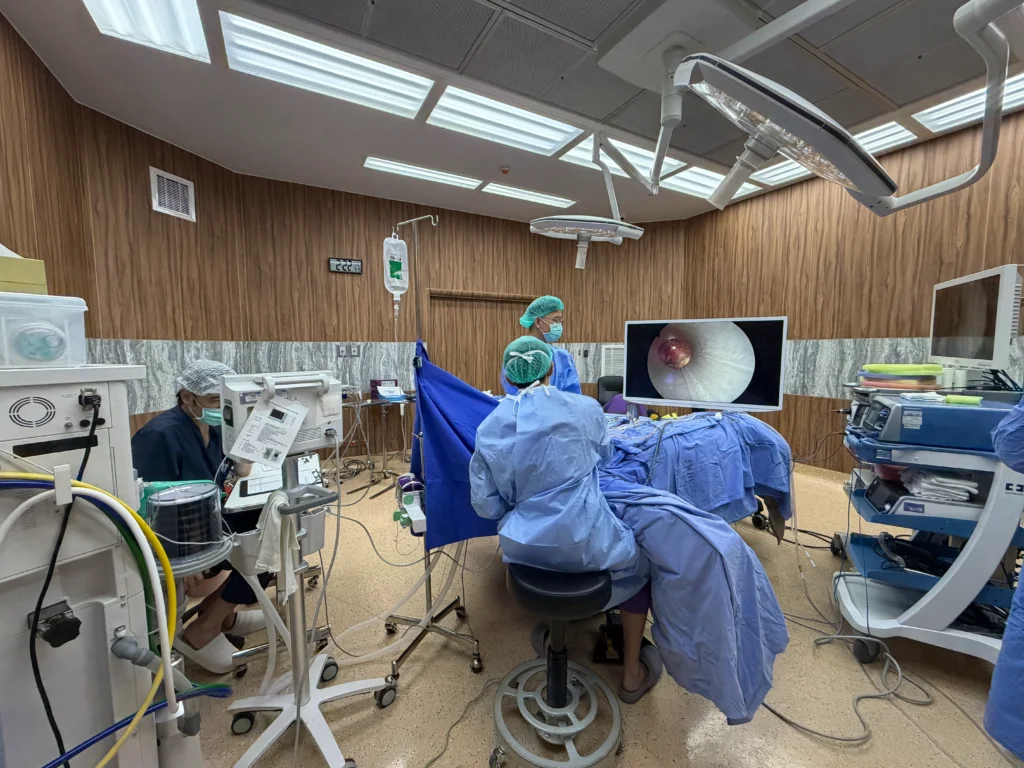
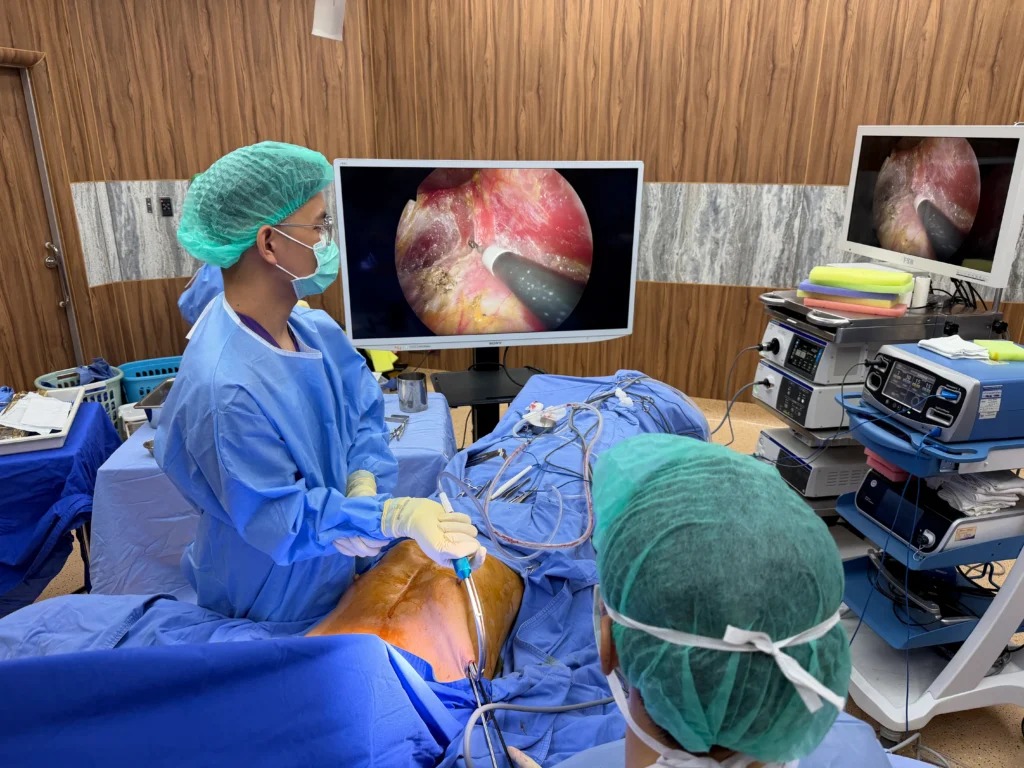
Endoscopic Transaxillary Breast Augmentation at WIH

For suitable patients who prefer an incision away from the breast, WIH offers endoscopic transaxillary augmentation through an underarm incision.

An endoscope provides a clear view of the operative pocket on a monitor, allowing dissection under direct visualization, control of bleeding and precise adjustment of the lower and lateral pocket boundaries.

When the lower breast is tight or the inframammary fold needs lowering, controlled release creates additional lower-pole space so the implant can sit at the planned level within the expanded pocket.

Dual-Plane Options Through Endoscopic Access

The standard approach used at WIH generally creates a Dual Plane Type I pocket through controlled release of the inferior pectoralis attachment. Types II and III can also be performed when indicated, using additional endoscopic dissection between the breast tissue and the anterior surface of the pectoralis muscle.

This additional separation extends upward from the inframammary fold to the lower border of the areola for Type II, or to the upper border for Type III, according to the required tissue adaptation.

transgender-operation-surgery

The consultation considers anatomy, scar preference and surgical cost when choosing between endoscopic transaxillary and inframammary access.

Precise pocket creation establishes the implant’s position; tissue healing and pocket stability then influence how the final breast shape develops.

Pocket Stability and the Final Breast Shape

The inframammary fold and lateral pocket boundary help support the implant at the planned level and limit excessive downward or outward movement as tissues heal.

Swelling and muscle tension may initially make the implants appear high. The final breast shape can generally be appreciated around 3–6 months after surgery, as the implants settle into the lower poles and the inframammary folds become more clearly defined. The aim is for both breasts to have similar contours and fold levels, although individual anatomy and healing may leave some asymmetry.

Healing and Follow-Up

Follow-up assesses healing, implant position, symmetry and breast softness, including signs of capsular contracture such as increasing firmness, distortion or discomfort. Postoperative care is adjusted to support recovery and maintain the intended pocket boundaries.

breast-augmentation-380cc-dr-chettasak-before-surgery

Before Surgery

breast-augmentation-380cc-dr-chettasak-after-surgery Post-op 8 years

After Surgery

Long-Term Breast Shape — Before Surgery and at 8-Year Follow-Up
Breast augmentation with 380 cc implants · Submuscular placement · Transaxillary (underarm) incision

How to Choose the Best Hospital for Transgender Breast Augmentation in Thailand

Choosing a hospital involves considering the surgeon’s experience with transgender breast anatomy, a clear explanation of surgical options and limitations, appropriate anesthesia and hospital support, and continuity of postoperative care.

Your consultation should address tissue coverage, chest proportions, nipple position and breast-fold planning. If you are considering revision surgery, it should also identify the existing problem and explain what correction can realistically achieve.

At WIH International Hospital in Bangkok, Thailand, our plastic surgery team provides individualized assessment and surgical planning, supported by coordinated hospital care and postoperative follow-up.

Whether you are considering your first breast augmentation or seeking revision of a previous result, contact the WIH team to discuss your goals, treatment options and recovery plan.

Request a Personalized Consultation

Email: info@wihhospital.com
WhatsApp: +66 95 650 3892

Request a Personalized Consultation

Email: info@wihhospital.com
WhatsApp: +66 95 650 3892

Email WIH WhatsApp LINE

Considering Revision Breast Surgery?

If you are concerned about a previous breast augmentation, the WIH surgical team can assess problems such as capsular contracture (breast firmness), asymmetry, bottoming out, high-riding implants, lateral displacement, symmastia (loss of separation between the breasts), or implant rupture.

Assessment focuses on identifying the underlying cause and discussing suitable corrective options, which may include implant exchange, capsule treatment or pocket reconstruction.

Breast implants are not lifetime devices. Your consultation also addresses surgical risks, implant-specific considerations and appropriate long-term follow-up.

Explore Revision Breast Surgery at WIH

Pocket Stability and the Final Breast Shape

The inframammary fold and lateral pocket boundary help support the implant at the planned level and limit excessive downward or outward movement as tissues heal.

Swelling and muscle tension may initially make the implants appear high. The final breast shape can generally be appreciated around 3–6 months after surgery, as the implants settle into the lower poles and the inframammary folds become more clearly defined. The aim is for both breasts to have similar contours and fold levels, although individual anatomy and healing may leave some asymmetry.

Healing and Follow-Up

Follow-up assesses healing, implant position, symmetry and breast softness, including signs of capsular contracture such as increasing firmness, distortion or discomfort. Postoperative care is adjusted to support recovery and maintain the intended pocket boundaries.

How to Choose the Best Hospital for Transgender Breast Augmentation in Thailand

Choosing a hospital involves considering the surgeon’s experience with transgender breast anatomy, a clear explanation of surgical options and limitations, appropriate anesthesia and hospital support, and continuity of postoperative care.

Your consultation should address tissue coverage, chest proportions, nipple position and breast-fold planning. If you are considering revision surgery, it should also identify the existing problem and explain what correction can realistically achieve.

At WIH International Hospital in Bangkok, Thailand, our plastic surgery team provides individualized assessment and surgical planning, supported by coordinated hospital care and postoperative follow-up.

Whether you are considering your first breast augmentation or seeking revision of a previous result, contact the WIH team to discuss your goals, treatment options and recovery plan.

Request a Personalized Consultation

Email: info@wihhospital.com
WhatsApp: +66 95 650 3892

[row_inner_3] [col_inner_3 span__sm=”12″ padding=”20px 30px 10px 30px” padding__sm=”20px 15px 10px 15px” margin=”0px 0px -19px 0px” bg_color=”rgb(255, 255, 255)” bg_radius=”20″]

Request a Personalized Consultation

Email: info@wihhospital.com
WhatsApp: +66 95 650 3892

Email WIH WhatsApp LINE
[/col_inner_3] [/row_inner_3]
breast-augmentation-380cc-dr-chettasak-before-surgery

Before Surgery

breast-augmentation-380cc-dr-chettasak-after-surgery Post-op 8 years

After Surgery

Long-Term Breast Shape — Before Surgery and at 8-Year Follow-Up
Breast augmentation with 380 cc implants · Submuscular placement · Transaxillary (underarm) incision

Considering Revision Breast Surgery?

If you are concerned about a previous breast augmentation, the WIH surgical team can assess problems such as capsular contracture (breast firmness), asymmetry, bottoming out, high-riding implants, lateral displacement, symmastia (loss of separation between the breasts), or implant rupture.

Assessment focuses on identifying the underlying cause and discussing suitable corrective options, which may include implant exchange, capsule treatment or pocket reconstruction.

Breast implants are not lifetime devices. Your consultation also addresses surgical risks, implant-specific considerations and appropriate long-term follow-up.

Explore Revision Breast Surgery at WIH

Frequently Asked Questions

Breast massage is individualized rather than routinely recommended for every patient. Based on his clinical experience, Dr. Chettasak may recommend carefully directed massage for selected patients to help maintain breast softness and manage tissue tightness.

Some studies have reported lower rates of capsular contracture with postoperative exercises, although findings are inconsistent and largely involve older implants and techniques. Massage is therefore considered one part of postoperative care rather than a guaranteed method of prevention.

Patients with adequate tissue coverage and a stable pocket without excessive tightness may not need routine massage. The decision also considers implant design, placement and healing. When recommended, the WIH team demonstrates the timing and technique, with particular care to avoid overstretching the lower or lateral pocket.

The fundamental techniques are shared. Differences in tissue coverage, chest width, nipple position, muscle and breast-fold anatomy can change the plan. Individual assessment determines the approach.

Many transgender patients have limited breast tissue. Placing the implant partly beneath the pectoral muscle provides additional coverage and helps create a smoother upper-breast transition.

For patients with substantial existing breast tissue and mild sagging (ptosis), subglandular placement—above the muscle—may be considered. More pronounced ptosis may require a breast lift to achieve the intended shape.

The choice is individualized according to tissue coverage, muscle anatomy, nipple position and the degree of sagging.

Implant projection describes how far the implant extends forward from the chest. At WIH, selection considers implant volume together with breast-base width, tissue coverage, chest proportions and nipple spacing.

For implants below 400 cc, Moderate Plus (Mentor) or Demi (Motiva) profiles are often considered. For implants 400 cc or larger, High (Mentor) or Full (Motiva) profiles may be suitable, depending on the patient’s anatomy and desired fullness.

These are planning preferences rather than fixed rules. A wide chest or wide nipple spacing requires careful assessment of implant width as well as projection; a higher profile alone does not correct wide nipple spacing.

Yes. In appropriately selected patients, the transaxillary (underarm) approach can achieve a breast shape comparable to the inframammary (breast-fold) approach, while placing the scar in the underarm rather than on the breast.

Transaxillary augmentation accounts for approximately 80% of WIH’s breast augmentation cases, reflecting the team’s extensive experience with this technique, including endoscopic surgery.

A surgeon experienced in different incision approaches can explain their suitability and limitations while maintaining the same goals for breast shape and implant position. At WIH, incision selection considers your scar preferences, lifestyle and anatomy, rather than simply following the surgeon’s preferred approach.

The inframammary fold (IMF) defines the lower breast contour. WIH surgeons plan its position around implant dimensions, nipple position, tissue support and existing asymmetry, aiming for balanced lower-breast proportions and closely matched fold levels.

When lowering the IMF is necessary, controlled release and careful pocket creation accommodate the implant while preserving support. The lower and lateral pocket boundaries help limit bottoming out—excessive downward movement—and lateral displacement, or outward movement.

If an inframammary incision is chosen, the scar is planned to align with the intended new fold, where it can be better concealed. Support garments, individualized activity instructions and follow-up help protect the pocket as it heals. The contour and fold levels are generally assessed more reliably at 3–6 months, although healing varies and displacement can still occur.

Yes. At WIH, this is a common combination for patients seeking breast feminization alongside genital gender-affirming surgery. Both procedures can be performed during the same general anesthetic, with breast augmentation typically adding approximately 1–2 hours to the operation, depending on the technique. Complex revision cases may require longer.

The team assesses your health, total operating time and recovery needs before recommending combined or staged surgery.

Breast implant-associated anaplastic large cell lymphoma (BIA-ALCL) is a rare lymphoma that develops in the fluid or scar capsule surrounding a breast implant. It is not breast cancer. The association is strongest with macrotextured implants, although cases have also been reported with microtextured implants. Risk varies between implant surfaces and products.

Motiva SmoothSilk implants, including Ergonomix2 used in the JOY program, are classified as smooth-surface implants, despite their fine surface microstructure. This classification should not be interpreted as a guarantee of zero risk.

Persistent swelling, a new lump or unexplained pain—particularly after the breasts have healed—should be assessed promptly. The WIH surgical team discusses implant-specific risks and long-term follow-up during consultation.

Cost depends on the implant, approach, equipment, corrective work and care arrangements. WIH provides a personalized quotation identifying the proposed procedure and what is included.